In 2009, researchers at UC Davis took old, ovariectomized mice (mice whose ovaries had been surgically removed early in life) and transplanted young ovaries into them. The mice were already past middle age. By any reasonable measure, they had months to live. And yet, the mice who received young ovaries lived up to 40% longer than controls.
The ovary is one of the fastest-aging organs in the human body (although the aorta and thymus do jockey for competition). A woman is born with approximately 1-2 million primordial follicles. These are the immature precursors to eggs, suspended in a kind of biological stasis in the ovarian cortex. By puberty, roughly 300,000-400,000 remain. Then, every month, a cohort of follicles “wakes up” and begins maturing. One becomes dominant and ovulates. The rest die through a process called atresia. Approximately 1,000 follicles are lost per month, regardless of whether a woman is on birth control, pregnant, or doing nothing at all. By age 30, about 90% of a woman’s follicles are gone. By menopause, fewer than 1,000 remain. What many in biotech and healthcare still fail to realize is that ovarian aging is not just a fertility problem; it is a systemic aging problem, and the data increasingly suggest that interventions targeting ovarian aging could be incredibly valuable not only for the extension of reproductive lifespan, but healthspan, too
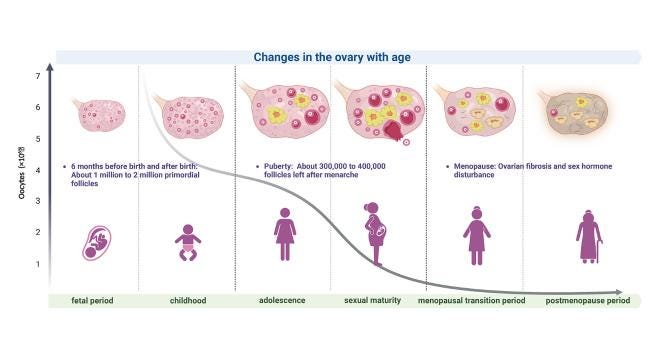
.
Reproductive aging is a topic I’ve been ruminating on for quite a while now. In high school, I conducted research on the therapeutic potential of a follicle-stimulating hormone (FSH) antibody in post-menopausal women (some of which I will detail below). Last summer, I presented to the Norn Group on advances in this field. This spring, I joined the Hattie Chung Lab at Yale as an undergraduate researcher, mapping which features of ovarian immune aging are conserved across humans and mice to (i) prioritize circuits that are truly translatable in preclinical models and (ii) identify therapeutic targets to delay ovarian immune aging and consequently sustain systemic healthy tissue remodeling. It always struck me how women live ~5.3 years longer than men, but spend more of those years in poor health. The reason why has eluded scientists for many years, and the field has begrudgingly resigned to the fact that the lifespan gap is multifactorial. Theories such as X inactivation escape, estrogenic cardiovascular and bone protection, and lower infection rates have all emerged as promising explanations. However, one fact about female aging is incontrovertible: menopause marks an inflection point that accelerates bone loss, cognitive decline, metabolic dysfunction, and cardiovascular disease. Later menopause strongly correlates with longer lifespan, and early ovariectomy in dogs erases the female survival advantage entirely.
The mechanistic story is becoming clearer. GWAS and animal models consistently implicate DNA damage response pathways as the primary regulators of reproductive senescence. CHEK2 knockouts show slower follicle depletion; DEPTOR loss-of-function variants (an mTOR inhibitor) accelerate menopause; HELB variants that restrict DDR repair delay it. At the cellular level, aged ovaries show decreased granulosa and theca cells, reduced vascularization, and upregulation of stress-responsive transcription factors like CEBPD.
One approach to combating menopause is to relieve its deleterious effects. HRT remains the gold standard for symptom management, and the pendulum has swung decisively back toward recognizing its benefits after the flawed Women’s Health Initiative created a generation of HRT-averse physicians. Modern formulations (transdermal estradiol, micronized progesterone) have far better safety profiles than the conjugated equine estrogens and synthetic progestins of the WHI era. But HRT has several limitations:
It replaces hormones exogenously rather than restoring endogenous ovarian function.
It cannot recreate the complex pulsatile, cyclical signaling that characterizes premenopausal physiology.
The “window hypothesis” suggests benefits diminish when initiation is delayed years beyond menopause onset.
Contraindications exclude many women who could benefit most (history of breast cancer, thromboembolism, certain cardiovascular conditions)
This is not to scare anybody off from HRT; the therapy has worked wonders for millions of women worldwide. But its failings create an incentive for novel therapies in the menopause space. I’ll insert here a shameless plug to my own high school research, which argued that FSH is a target worth pursuing (Full essay here). While the deterioration brought upon by menopause has long been blamed on estrogen depletion, recent research suggests a second negative contribution by follicle-stimulating hormone; FSH levels spike dramatically during menopause and contribute independently to bone loss, visceral fat accumulation, metabolic dysfunction, and possibly neurodegeneration. The Zaidi Lab’s MS-Hu6 antibody, which blocks FSH action, has shown great efficacy in preserving bone mass, preventing adiposity, and improving cognitive performance in animal models. If Phase I confirms the safety profile and confirms the signals seen in mice, MS-Hu6 could become a multi-indication therapeutic for osteoporosis, obesity, and potentially neurodegenerative conditions, three disease states that cluster in postmenopausal women and share FSH as a common upstream driver.
Yet another strategy resolves to slow the aging of the ovary itself.
I first came across this class of approach upon reading about the 2023 VIBRANT pilot trial run by Dr. Yousin Suh at Columbia Fertility, which evaluated a 5 mg per week dose of rapamycin in premenopausal women. Rapamycin, an mTOR inhibitor originally developed as an immunosuppressant, has become the darling of the longevity field for good reason: it extends lifespan in nearly every model organism tested, and its safety profile across decades of transplant medicine is thoroughly characterized. mTORC1/2 inhibition preserves ovarian function and fertility in premenopausal women undergoing chemotherapy; in mice, chronic mTOR suppression inhibits age-related ovarian surface epithelium hyperplasia. In 2019, Garcia et al. found that calorically restricted and rapamycin-treated female mice both display more primordial follicles, fewer maturing follicles, and increased ovarian Foxo3a expression.
The VIBRANT trial (funded by Impetus Grants, brainchild of the incredible Martin Borch Jensen and Lada Nuzhna, two Longevity Fund/age1 portco founders) proved highly promising; preliminary results from 34 participants suggest a 20% reduction in ovarian aging, with follicle activation dropping from roughly 50 eggs per month to 15. Meanwhile, a 2025 IVF trial in China demonstrated that even 1mg daily rapamycin for 3-4 weeks before egg retrieval in 100 reproductive-aged women significantly improved embryo quality, doubling blastocyst development. The cumulus cells surrounding eggs showed the most dramatic age-related decline, as rapamycin appears to rebalance protein recycling and oxidative stress defense in these support cells. Rapamycin pretreatment raised the post-embryo transfer clinical pregnancy rate to 50%, compared with 28% in the control group, a remarkable result for just a 21-28 day protocol.
Other strategies being explored by academia and biotech include follicle activation control (AMH), induction of oocyte dormancy (FOXO3), tissue remodeling (anti-fibrotics), targeting innate immune inflammation (inflammasome-linked pathways), restorative approaches (cryopreservation/autologous transplantation, regenerative and cell therapy strategies), and more.
Industry players
Gameto has emerged as a category leader with $127 million raised and the most advanced clinical program. Their Fertilo product, iPSC-derived ovarian support cells that mature eggs ex vivo, has achieved first-in-human live births and is now in Phase 3 trials in the US after FDA IND clearance in January 2025. The technology reduces IVF hormone injections from 14 days to 2-3 days and has been commercialized across Peru, Mexico, Australia, Japan, Gameto, and six additional countries.
More intriguing is Gameto’s Ameno program, an implantable cell therapy to restore ovarian hormone production and a next-generation vaginal ring for cyclical hormone release, making menopause “slow and gradual” rather than abrupt. The program received a $10M ARPA-H Sprint for Women’s Health grant in 2025 to advance the therapy, which is currently in preclinical development. Cell therapy is technically demanding with significant manufacturing, immunogenicity, and durability risks, but if Gameto can execute, their platform would be the first to restore endogenous ovarian signaling rather than simply replacing hormones exogenously.
Oviva Therapeutics was acquired by Granata Bio in April 2025, validating commercial interest in the AMH-mimetic space. Their lead candidate, OVI-586, is a first-in-class recombinant Anti-Müllerian Hormone. The biological rationale is clean: AMH naturally inhibits primordial follicle activation, so supplementing it should keep more follicles in reserve longer. Granata Bio plans to advance to human trials initially for IVF, with menopause delay as the larger eventual indication.
Celmatix has been around since 2009 and has raised somewhere in the range of $43-88M. They’ve pivoted from fertility genomics to therapeutics, with an AMH agonist program in the pipeline.
Ovarian Tissue Cryopreservation may sound sci-fi-esque, yet it has been clinically validated with over 130 births and no graft-related malignancies. The technology was largely developed by Yale’s Dr. Kuluk Oktay and consists of laparoscopically harvesting ovarian cortex strips, cryopreserving them, and later autotransplanting them. Modeling suggests harvesting 25% of the ovarian cortex at age 25 could delay menopause by 12–15 years.
This list is undoubtedly incomplete; there are far more approaches in the ovarian aging space than I could go into depth about here before losing a reader’s attention span, but suffice to say, there is plenty of room for innovation. Yet another subfield of reproductive aging biology aims to maintain fertility despite ovarian aging: Vitra Labs, Ovo Labs, Future Fertility, Alife, IVFmicro, and Coneption, just to name a few, tackle the problem of ovarian aging through in vitro gametogenesis, precise embryo selection, and a microfluidic culture system. But this set of approaches warrants a whole other article. If that’s a piece anybody wants to read, please comment below; I’m always looking for an excuse to learn more!